Learn how unparalleled data, domain expertise, and technologies enable AI-powered solutions that are purpose-built for healthcare.
For decades, pharma’s engagement model has pursued a familiar ambition: delivering the right information to the right stakeholder at the right time. Generative AI now offers healthcare professionals (HCPs) a version of that promise directly. They can ask a question in their own words and receive a synthesised response within seconds.
In earlier IQVIA work, we described AI as becoming a “front door” to medical information, helping clinicians orient themselves, surface relevant evidence and compare options, often before traditional engagement occurs.1 That front door is now reality. In a 2026 IQVIA survey of 23,769 physicians across 34 markets, 80% reported using at least one AI tool, while almost half used AI daily or several times a week.2
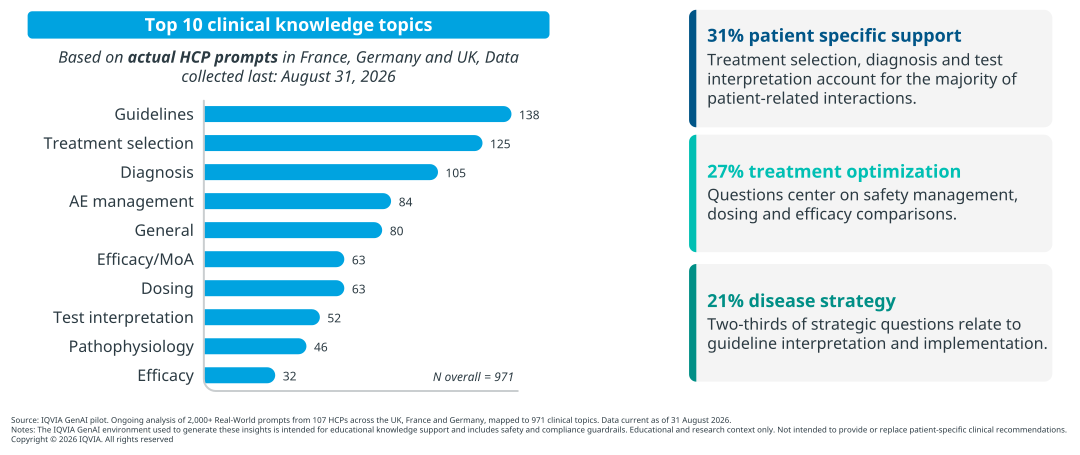
Its role is also extending beyond information retrieval. IQVIA’s ongoing analysis of more than 2,000 real-world HCP prompts from 107 HCPs across France, Germany and the UK shows that many of the questions being put to GenAI are already linked to clinical decision making. Guidelines remain the largest single topic, but treatment selection and diagnosis follow closely, alongside adverse-event management, general, efficacy, dosing and test interpretation (Figure 1).3 Almost one-third of the clinical topics identified are patient-specific. This suggests HCPs are not only asking what the evidence says. They are also asking how it applies in a particular patient or clinical situation. The questions increasingly reflect real decision points around treatment choice, patient fit, risk, timing and the strength of the supporting evidence. Clinical judgement remains with the HCP, but GenAI is moving closer to the point where evidence is interpreted and used.
Figure 1: HCP real-world prompt analysis; Source: IQVIA GenAI pilot. Ongoing analysis of 2,000+ real-world prompts from 107 HCPs across the UK, France and Germany, mapped to 971 clinical topics. Data current as of 31 August 2026.
Notes: The IQVIA GenAI environment used to generate these insights is intended for educational knowledge support and includes safety and compliance guardrails. Educational and research context only. Not intended to provide or replace patient-specific clinical recommendations.
This changes the sequence of engagement rather than replacing established channels. Pharma remains central to evidence generation and scientific dissemination, but an HCP may now put a question to a large language model (LLM) before consulting a publication, medical website or MSL.
For pharma, this creates both a potential blind spot and a source of insight. The initial framing of a question may happen outside traditional channels companies can manage or measure, while the questions asked and answers returned can reveal emerging needs, uncertainty and gaps in how evidence is represented.
Understanding this new layer requires two complementary perspectives: what HCPs are asking and how AI systems are answering.
Two complementary perspectives: what HCPs ask and how AI answers
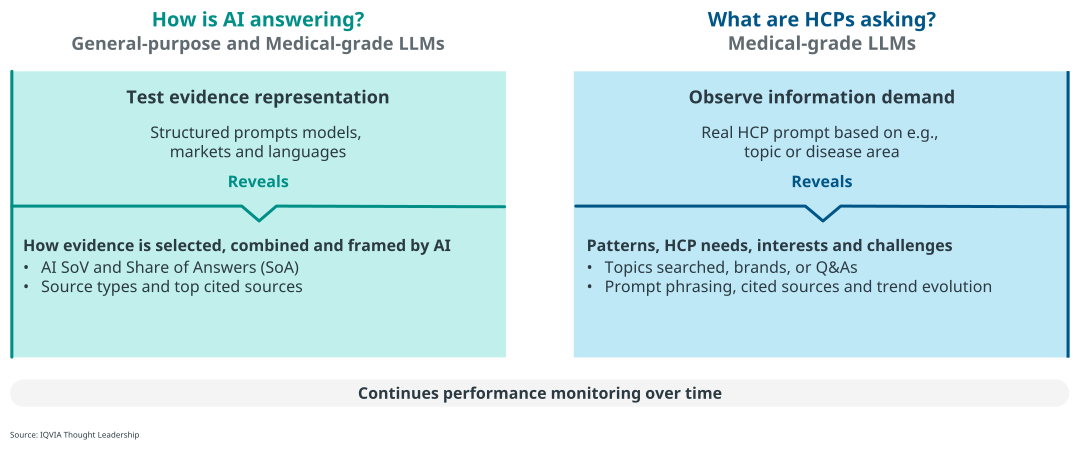
HCPs use a growing range of AI tools, from general-purpose LLMs such as ChatGPT, Gemini and Copilot to specialist clinical platforms and AI built into institutional workflows. The difference is not simply that specialist tools provide better clinical information. Recent evaluations suggest that leading general-purpose models can perform just as well on some clinical information tasks4. Specialist platforms may differ more in how they support clinical practice, for example through AI scribing and documentation, decision support and integration with electronic health records. As these platforms become more embedded in clinical workflows, they are also more likely to reflect the needs and systems of a particular institution or health system. The boundaries are also beginning to blur as these platforms expand from documentation into information retrieval and decision support, potentially shifting some interactions from explicit HCP prompts towards information surfaced from the clinical context itself. For pharma seeking to understand this new information environment, the more useful distinction is not between individual tools, but between two complementary sources of insight: what stakeholders are asking and how AI is answering. Figure 2 summarises the two perspectives.
Figure 2: Two complementary insights from GenAI models; Source: IQVIA Thought Leadership
How is AI answering? Pharma teams can use structured, persona-based prompts to test questions that HCPs, patients and payers may bring to an AI conversation. They can then assess the answers for source citations, treatment framing, share of answers and visibility gaps against competitors, revealing how diseases, brands and evidence are represented across models, markets and languages.
What are HCPs asking? Where participating medical platforms make consented, governed prompt data available, IQVIA can analyse which questions HCPs ask, how topics evolve, which specialties or markets drive activity, and what information is surfaced in response. This offers a more direct view of real-world information needs as they emerge, complementing surveys and retrospective research.
Taken together, these two perspectives allow pharma to move beyond a narrow question, “Are we present in the answer?”, and ask a more useful one: “What does the answer reveal about stakeholder needs, the available evidence and the action required?”
From GEO to decisions across the brand lifecycle
Much of the industry’s early work has focused on generative engine optimisation, or GEO: helping credible evidence to be found, interpreted and cited in AI-generated answers. This is an important starting point. LLMs do not simply rank sources; they combine them into a response. Source authority, clinical relevance and content structure therefore influence both whether evidence appears and how it is represented. Earlier IQVIA work described this as earning “algorithmic trust”.
The larger opportunity lies in connecting the question with the answer. Seen together, they show whether relevant evidence is visible and whether it addresses the need behind the question. Tracking these patterns over time can reveal where uncertainty is growing, where new evidence is changing the discussion and where older narratives continue to shape the response.
This complements primary market research rather than replacing it. PMR provides the structure and depth to test hypotheses, explore motivations and understand how widely a need is shared. LLM-derived insight adds a more continuous signal between research waves, based on questions HCPs raise naturally rather than only those anticipated in a research brief. It can help teams identify an emerging issue earlier, then investigate it through PMR, field insight and other established sources.
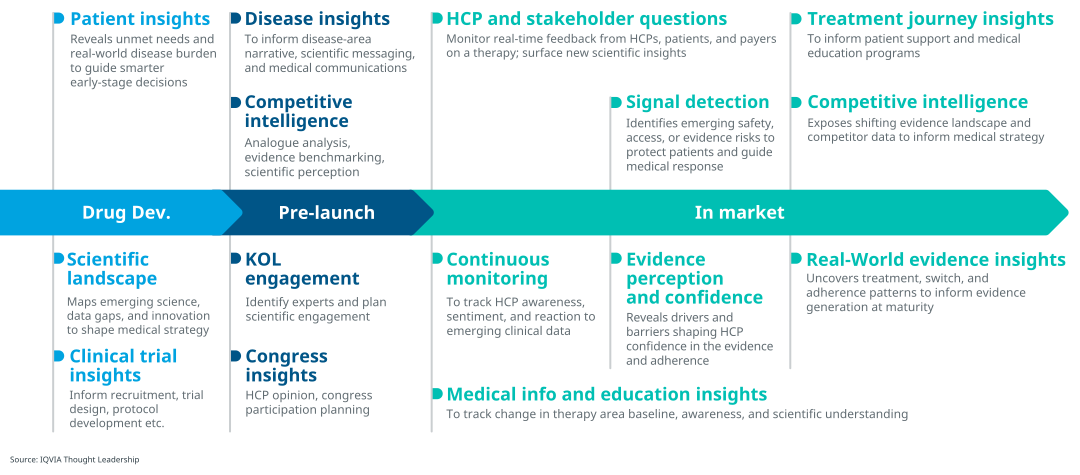
The value extends across the brand lifecycle (Figure 2). During development, recurring questions can sharpen understanding of unresolved clinical needs and help test evidence priorities. Around launch, differences by market or specialty can inform publication planning, medical education and field readiness. For in-market products, teams can assess whether new evidence, guideline updates or company-led communications and campaigns are changing both the questions HCPs ask and the answers AI provides.

Figure 3: From AI visibility to decisions across the lifecycle; Source: IQVIA Strategy Consulting
Building this capability requires more than a one-off visibility assessment. It requires repeatable analysis, continued tracking and a way to connect emerging signals with the teams able to respond. IQVIA can bring together governed data from specialist medical platforms, controlled analysis of general-purpose LLMs and expertise across research, evidence and engagement.
The implication is that pharma should not treat AI simply as another channel to optimise. It should learn continuously from the information exchange that AI now mediates, linking stakeholder questions and AI-generated answers to evidence strategy and engagement decisions.
When AI answers first
When AI answers first, pharma’s role does not disappear. It becomes more demanding. Companies must still generate credible evidence and communicate it responsibly through established medical and commercial channels. They must now also understand how that evidence is selected, combined and framed by systems they do not control.
The familiar ambition of delivering the right information to the right stakeholder at the right time therefore remains valid. What changes is the route. In an AI-mediated environment, success depends on making credible evidence easier to find and represent accurately, while learning from the questions HCPs ask and the answers they receive.
Success will not come from appearing in every answer. It will come from recognising earlier where stakeholder questions, available evidence and current understanding no longer align, and adapting evidence and engagement accordingly.
AI may increasingly provide the first answer. Pharma’s advantage will come from knowing when that answer is not good enough, why it falls short and what needs to change.
Navigating AI search and visibility in pharma
Key questions on GEO, AI-generated answers and the evolving healthcare information landscape
References
1 Scott K, Alzaga-Chaudhry C. The evolution of pharma engagement as AI becomes a front door to medical information. IQVIA, March 2026.
2 IQVIA Use of AI Tools Channel Dynamics Survey, May to July 2026. Survey base: 23,769 physicians across 34 markets.
3 IQVIA analysis of 2000+ HCP prompts across France, Germany and the UK. Data collected to 31 August 2026.
4 Beaulieu-Jones, B., Nemati, S. Limited benchmarks constrain the conclusions of a general-purpose versus clinical AI comparison. Nat Med (2026). https://doi.org/10.1038/s41591-026-04638-6